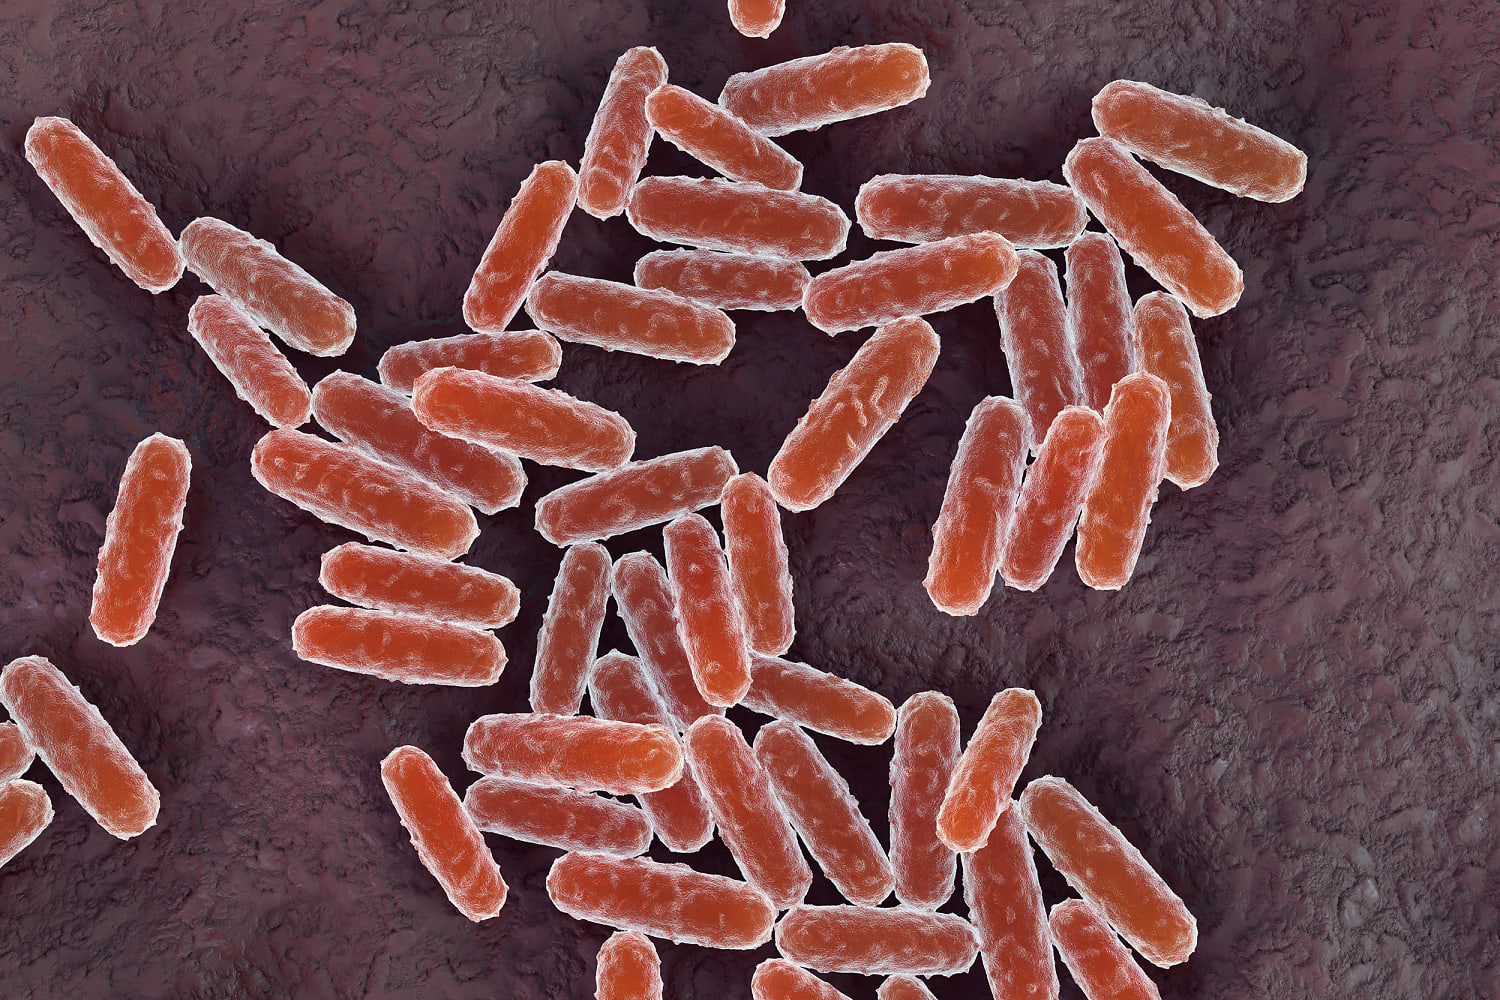
Pneumonic plague is the most virulent and lethal form of plague, caused by the bacterium Yersinia pestis, and it demands immediate global health attention following fatal infection reports originating in Russia. Unlike bubonic plague, which spreads primarily through flea bites and infects the lymphatic system, pneumonic plague attacks the respiratory tract directly and spreads rapidly from person to person through respiratory droplets. This primary pulmonary infection carries a near-certain mortality rate if antibiotic administration does not occur within the first twenty-four hours of symptom onset, making any isolated case an immediate public health emergency.
The Mechanism of Yersinia Pestis
Bacteria do not respect international borders, nor do they care about modern geopolitical boundaries. When Yersinia pestis enters the human lung tissue, it triggers a devastating inflammatory response combined with systemic shock. In related news, we also covered: Institutional Containment Failure at Biosafety Facilities.
The incubation period is terrifyingly short, often ranging from twenty-four to seventy-two hours. Patients experience sudden-onset high fever, chills, headaches, and a rapidly worsening cough that produces bloody sputum.
Without aggressive intervention using specific aminoglycosides or fluoroquinolones, respiratory failure and circulatory collapse follow swiftly. Modern medicine has the tools to treat the infection, but logistical failures in early diagnosis remain the primary vulnerability in containment strategies. CDC has provided coverage on this fascinating topic in great detail.
Historical Context and Modern Vulnerabilities
History reminds us that this pathogen shaped empires and destroyed populations. The Black Death of the fourteenth century stands as the most famous manifestation, yet plague never truly vanished. It persists in natural animal reservoirs across parts of Central Asia, the Americas, and Africa, where wild rodents and their fleas maintain the enzootic cycle.
When humans encroach upon these ecosystems or handle infected wildlife, sporadic spillover events occur. The Russian case underscores a persistent reality: rural isolation, delayed medical presentation, and initial misdiagnosis by frontline practitioners allow a treatable bacterial infection to transform into a lethal crisis.
Diagnostic delays happen because clinicians rarely encounter plague in routine practice today.
The Anatomy of Silence When Pneumonic Plague Returns
health, news
Infectious disease reports rarely begin with a whisper, but they often end with an institutional scramble. When a fatal case of pneumonic plague surfaced in Russia, the initial wave of international news followed a familiar cadence. A headline. A vague mention of a mysterious illness. A quick nod to medieval history designed to provoke anxiety rather than clarity.
Pneumonic plague is the most severe and rapidly progressive form of Yersinia pestis infection, transmitted directly through respiratory droplets and carrying near-certain mortality if treatment fails within the first twenty-four hours. This is not a dormant ghost from the past waiting for a cinematic moment to reappear. It is an enduring, naturally occurring pathogen tucked into rodent reservoirs across multiple continents, maintaining a constant presence in global ecosystems while public health surveillance systems oscillate between complacency and overreaction.
Look past the panic-driven framing of recent viral outbreaks and a more complex structural reality emerges. Modern epidemiological tracking is vastly superior to what it was a century ago, yet our geopolitical and logistical frameworks for containing localized vector-borne threats remain brittle. When a single vector slips through containment, the failure is rarely biological. It is systemic.
The Pathogen Beneath the Narrative
Yersinia pestis operates on an evolutionary timeline that treats human panic as background noise. To understand why a fatality in Eastern Europe triggers global apprehension, one must look at how the bacterium moves through host populations. Sylvatic reservoirs—wild rodent populations carrying the bacteria and their associated fleas—are distributed across vast swaths of Central Asia, the American West, parts of Africa, and South America.
Bubonic plague is the most common manifestation, acquired through flea bites or direct contact with infected tissue, presenting with swollen lymph nodes known as buboes. Septicemic plague occurs when the bacteria multiply in the blood, leading to tissue necrosis and organ failure. Pneumonic plague, however, is the terrifying outlier. It happens when the infection reaches the lungs or when a patient with bubonic or septicemic plague develops secondary pneumonia, allowing the pathogen to spread directly from person to person via airborne droplets expelled by coughing.
The window for intervention is ruthlessly narrow. Aminoglycosides and tetracyclines remain highly effective antibiotics, but they must be administered almost immediately upon symptom onset. Fever, headache, weakness, and rapidly developing pneumonia with bloody sputum can escalate to respiratory failure within hours. When a case emerges in an urban center or a monitored region, the immediate medical priority is not just treating the individual, but tracing every possible contact before the transmission chain multiplies exponentially.
+-------------------------------------------------------------+
|               YERSINIA PESTIS MANIFESTATIONS                 |
+--------------------+-------------------+--------------------+
| Form               | Transmission Route| Mortality (Untreated)|
+--------------------+-------------------+--------------------+
| Bubonic            | Flea bite / Contact| 30% - 60%          |
| Septicemic         | Bloodstream       | Near 100%          |
| Pneumonic          | Respiratory drops | Near 100%          |
+--------------------+-------------------+--------------------+
Surveillance Gaps and Regional Vulnerabilities
Public health analysts tend to categorize outbreaks into two groups: those that make headlines and those that do not. Endemic regions in parts of Madagascar, the Democratic Republic of Congo, and rural pockets of Central Asia report sporadic cases annually. These cases are managed through localized antibiotic distribution and vector control. They rarely capture the attention of international wire services unless a geopolitical friction point exists or a traveler crosses an international border.
When a fatal case occurs in a nation with advanced scientific infrastructure, the reporting often focuses on the mystery rather than the machinery of containment. This creates a dangerous information vacuum. The mystery is rarely how the bacterium exists—nature maintains that balance quite efficiently—but rather how modern supply chains, border controls, and municipal health agencies respond to the initial spark.
Consider the logistics of isolation and contact tracing in a major metropolitan area. If a patient presents with atypical respiratory symptoms that mimic severe influenza or viral pneumonia, standard diagnostic panels do not immediately screen for rare bacterial zoonoses. Pathogen identification requires specific laboratory protocols, fluorescent antibody testing, or culture confirmation. During that diagnostic lag, healthcare workers and family members are exposed.
This is the vulnerability point that epidemiological modelers worry about far more than the total case count. A single misdiagnosed case in a transit hub can transform a localized zoonotic spillover event into an international contact-tracing nightmare.
The Misinformation Echo Chamber
Every time Yersinia pestis enters the media cycle, digital platforms undergo a predictable transformation. Sensationalist accounts strip away biological nuance, trading clinical reality for apocalyptic imagery. This polarization serves neither public safety nor scientific literacy.
When people are told that a mysterious illness is sweeping a nation, their baseline trust in public health messaging erodes. They either dismiss the threat entirely as media exaggeration or overcorrect by hoarding prophylactic medications that are ineffective or unnecessary for plague prevention.
Public health communication requires absolute candor about uncertainty. When an agency says it is monitoring a situation, citizens deserve to know what indicators are actually being tracked:
- Vector Index: Are local flea populations showing rising bacterial loads?
- Contact Radius: How many secondary contacts have been identified and placed on prophylactic antibiotics?
- Genomic Sequencing: Does the strain show any unexpected resistance markers, or is it standard wild-type Yersinia pestis susceptible to common first-line treatments?
Without these metrics, reporting degenerates into speculation.
The Real Cost of Institutional Amnesia
Humanity has lived alongside this bacterium for millennia. The Justinian Plague, the Black Death, and the Third Pandemic shaped the demographic, economic, and cultural trajectories of civilizations. Yet modern societies suffer from a persistent institutional amnesia, assuming that advanced sanitation and antibiotics have permanently relegated infectious scourges to the history books.
Antibiotics changed the equation from absolute fatality to manageable infection, but they did not eradicate the ecological niches where the bacteria thrive. Climate shifts, agricultural expansion into wild habitats, and changing rodent migration patterns ensure that human-animal interfaces remain active. Every time a forest is cleared, a highway cuts through a grassland, or a climate anomaly alters rodent feeding behaviors, the probability of human exposure changes.
Treating a plague case in the twenty-first century is clinically straightforward. Preventing institutional panic when that case makes the news remains an unsolved puzzle. The Russian incident should not be viewed as an isolated anomaly or a dark omen of things to come. It is a recurring reminder that human civilization shares a biosphere with ancient, highly adaptable microorganisms that require constant vigilance, transparent data sharing, and robust primary healthcare infrastructure.
The next time a headline warns of a mysterious illness traced back to a forgotten pathogen, look past the adjectives. Ask about the surveillance data. Ask about the antibiotic stockpiles. Ask about the frontline workers who quietly keep the machinery of containment running long after the news cycle has moved on to the next panic.